
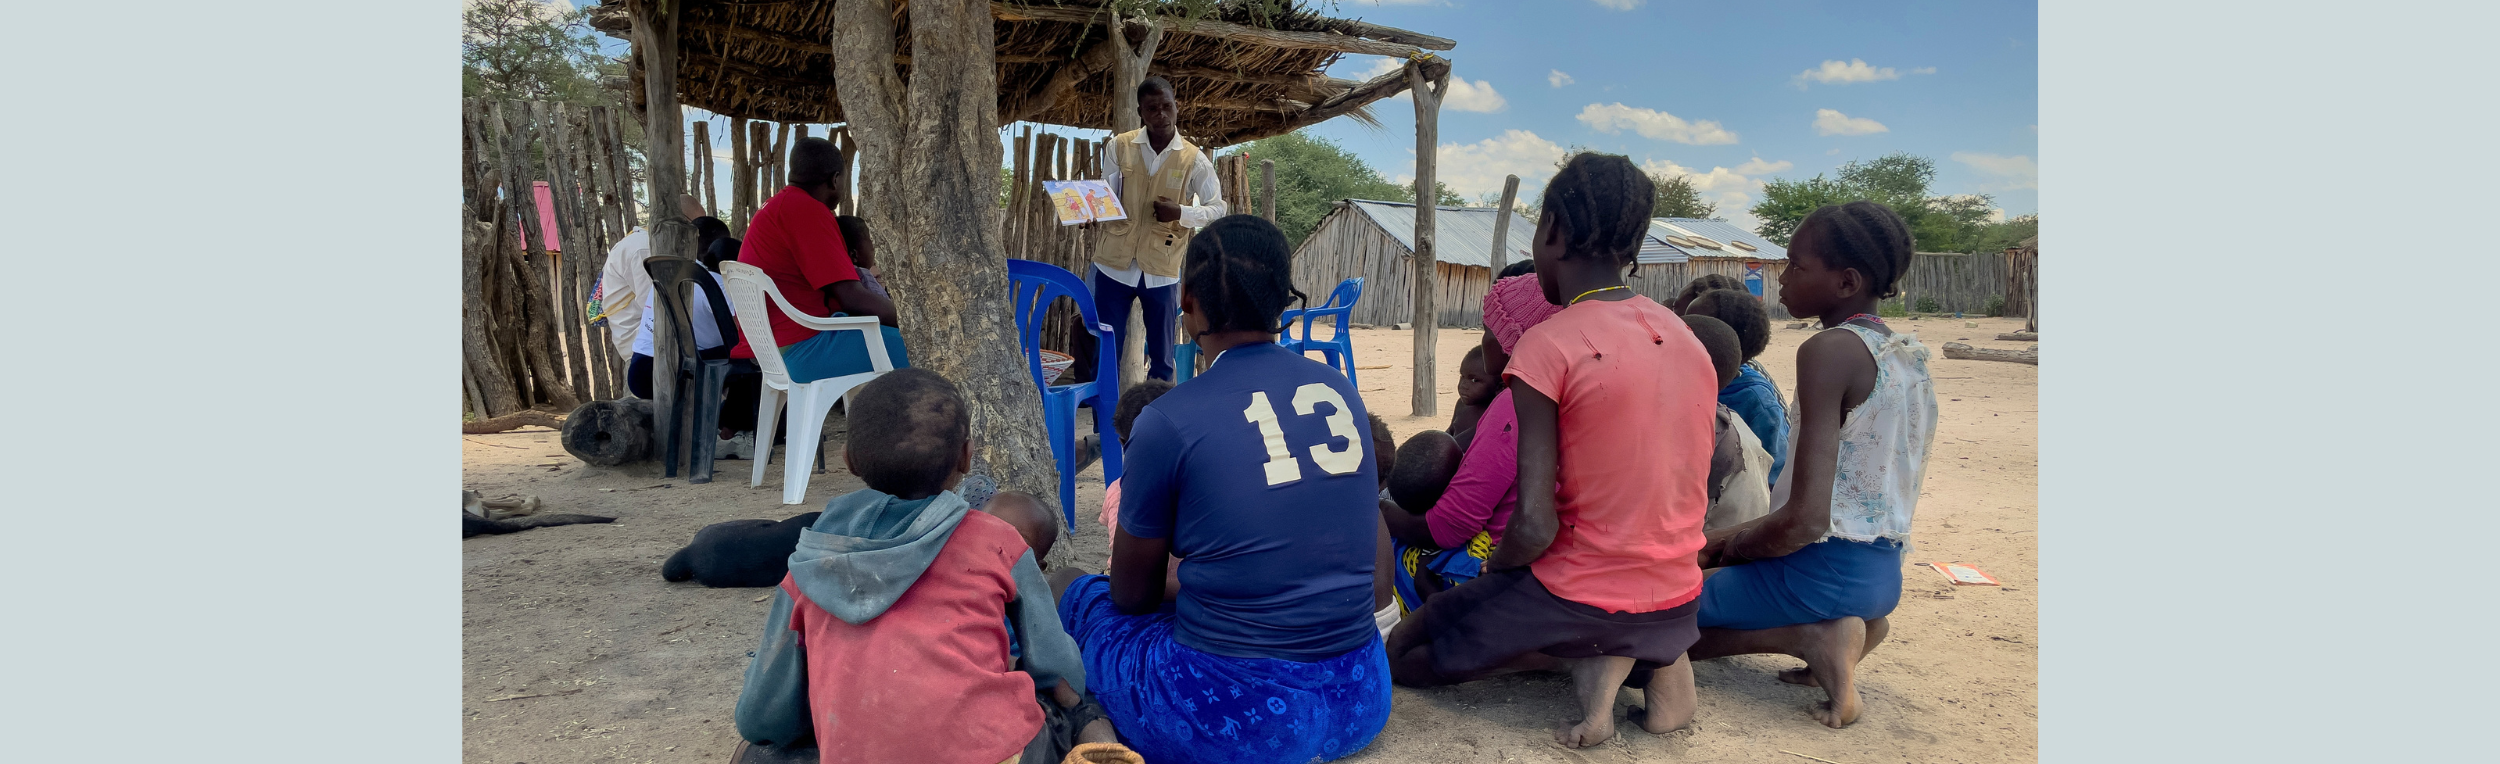
In the communities of Cahama, Humbe, and Ombadja, in southern Angola, change also happens through words. Those spoken by the Community Health Workers (CHWs) who meet families every day, visit their homes, organize awareness campaigns, and work to turn advice and information into new habits, thanks to the “START” project, funded by the European Union and implemented alongside Adespov and Codespa.
When Rodrigues, a CHW in Mbulutue, started working on the project, things were very different. Mothers did not give eggs to their children, and diets were less varied; they brought their children to the health post less frequently and paid little attention to hand hygiene. Today, he says, something has shifted. Families listen, ask questions, and are beginning to trust health workers more. Visits to the kimbandeiro—the traditional healer—have also decreased, and with them, cases of malnutrition.
Sometimes, change comes from a very simple gesture. A few days ago, Rodrigues met a mother whose child had been suffering from diarrhea for several days and who had no way to reach the hospital. He taught her how to prepare an oral rehydration solution at home. The woman later returned to thank him: she had discovered that she could take action to help her child even without medicine or a healthcare facility nearby.
Health, however, is not just about treatment. It is also about prevention and being able to identify a risky situation in time. Wilson, in Munkhete, talks about meeting women who, before the CHWs arrived, did not seek prenatal check-ups out of fear or lack of information. One of them had given birth at home. Wilson explained the importance of taking her baby girl to the hospital for her first vaccinations and to get a child health card. Later, that same woman began encouraging other mothers to give birth at the hospital.
Hygiene habits are changing, too. Families have learned to use safe places for defecation and to pay greater attention to cleanliness at home. When they asked for bleach to make water safe to drink, Wilson explained that boiling it first is also an option—a simple action that helps prevent diarrhea, especially in children.
Then there are deeply rooted beliefs that are difficult to change. One of these concerns breastfeeding: when some women found out they were pregnant again, they would stop breastfeeding their youngest child, convinced it was necessary. Today, Wilson says he is starting to see pregnant women continue to breastfeed. “And that makes me happy.”
Malnutrition is another area where the work of CHWs yields visible results. Maquina, in Ompupa, speaks of the satisfaction of seeing children who previously suffered from SAM (Severe Acute Malnutrition) back in good health after visiting their families. Here, too, change happens through education. Some families, for instance, used to reserve chicken meat exclusively for the father. Meetings on gender equality have helped challenge this tradition. Furthermore, in his micro-area, almost every family is now building a latrine. “I am very proud because today my community is rich in knowledge,” says Maquina.
Neusa, in Kavalawa, remembers how difficult it was at first to make people understand the severity of malnutrition. Today, she sees children improving, families changing, and mothers thanking her. Ester, on the other hand, learned how to perform nutritional screening through the project itself—a skill she did not have before, which now allows her to take concrete action in her community.
Above all, CHWs support women throughout pregnancy and childbirth. In Humbe, Jorge shares the story of a woman with a history of miscarriages who, after attending a session on pregnancy, came to him for help. He guided her through prenatal check-ups and advised her to go to the Chiulo hospital. The woman followed his guidance, carried her pregnancy to term, and had a normal delivery. She later returned with her baby to thank him.
Paulina has also seen a radical shift in the habits of women in her community. When she started working, many still gave birth at home. Today, she says, that no longer happens: women have understood the importance of going first to the waiting home and then delivering at the hospital.
Georgina recalls a pregnant woman who was bleeding and was afraid to go to the hospital. She explained to her that waiting could be dangerous for both her and the baby. The woman trusted her, began attending regular check-ups, and today her child is two years old and doing well.
Paulo tells a similar story. A woman had lost babies during previous pregnancies after experiencing bleeding between her second and fourth months. He encouraged her to seek care at the hospital and stayed in touch with her after every visit. In the end, the woman was able to have a child. Today, whenever she sees him, she thanks him with a smile.
Sometimes, supporting a family means not giving up at the first refusal. That is what happened to Sangue in Chiulo. He met a mother whose child, Tchapalama, had severe acute malnutrition with MUAC (mid-upper arm circumference) 9, SAM, and edema. The woman initially refused to take him to the hospital. Sangue involved other community members, spoke with the child’s aunt and father, and, together with the CUAMM team, managed to convince the father to go. The child was admitted to the ITFC (Inpatient Therapeutic Feeding Center). After an initial period of resistance, the mother also returned and accepted the situation. Today, when Sangue visits her, she asks him many questions. And the child is doing well.
Trust is perhaps the most significant outcome of this work. Cristina, in Hoji Ya Henda, accompanied a mother who was afraid to take her child with SAM to the health post, staying by her side during visits and helping her obtain medication. The child recovered. Grateful, the mother started calling her “fiancée,” saying she had saved her child’s life. “I get emotional every time she calls me that,” says Cristina. “And it makes me understand the importance of my work even more.”
Change also involves men and family dynamics. Idosio, in Manambonde 2, was initially afraid to talk about gender equality during awareness sessions because men did not want to listen. Today, however, he shares a concrete example of transformation: fathers are accompanying their children to get vaccinated and helping their wives with household chores.
Barnabè, in Tchemanha, tells the story of a pregnant woman who did not want to attend check-ups. After trying to schedule an appointment without success, he went to her home and offered to accompany her. He supported her until the birth of her baby and continues to accompany her for vaccinations. “What moves me the most is that she always waits for me with a smile.”
These are different stories, but they share a common thread: change does not come only from the hospital or the health post. It reaches homes, courtyards, happens during a conversation, through a visit, or an awareness campaign. It arrives when a mother decides to take her child for vaccinations, when a woman chooses to give birth in a hospital, when a family builds a latrine, or when a father begins to help his wife.
“We, the community health workers, are the primary agents of change,” says Celma, in the Tchipeke 2 district. And to be one, she adds, you must also lead by example, sharing with your community what you do every day at home.
This is perhaps the core strength of CHWs: being an integral part of the community they support, knowing its people and their daily struggles, speaking their language, and building—one encounter at a time—the trust that can turn knowledge into action, and action into a real opportunity for a healthier life.


